
Chapter 15
Irradiated, washed and CMV-tested blood components
Last updated: 2026-11-03
Key messages
Summary of key messages in this chapter:
-
Transfusion-associated graft versus host disease (TA‑GvHD) is rare but almost universally fatal—prevention relies on appropriate cellular blood component modification (irradiation or pathogen-reduction), not on recipient immunosuppression alone.
-
Pathogen‑reduction (psoralen‑treatment) of platelets prevents T‑cell proliferation; therefore, irradiation is not required.
-
Washed blood components should be reserved for specific indications such as severe allergic reactions, confirmed anti‑IgA–mediated anaphylaxis, or potassium reduction in high‑risk patients.
-
In Canada, leukoreduced blood components are considered CMV‑safe and equivalent to CMV‑seronegative products across all clinical indications.
-
Selection of irradiated, washed, or CMV‑safe components should balance patient risk, clinical evidence, and operational feasibility to deliver the safest transfusion.
Learning Objectives
After reading this chapter you will be able to:
-
Explain the pathophysiology, clinical features, and prevention of transfusion‑associated graft‑versus‑host disease (TA‑GvHD), including the role of irradiation and pathogen‑reduction technologies.
-
Identify patient populations and clinical scenarios that require irradiated blood components and apply current Canadian standards and NAC recommendations to component selection.
-
Describe the indications, preparation methods, limitations, and risks of washed red blood cells and platelets, including considerations related to allergic reactions, IgA deficiency, potassium reduction, and component expiry.
-
Compare CMV‑reduction strategies for blood components, including leukoreduction, CMV‑IgG seronegative donor testing, and pathogen‑reduced platelets, and apply current Canadian guidance regarding CMV‑safe products.
-
Integrate clinical, laboratory, and system‑based factors (e.g., patient risk, product availability, processing time, regulatory requirements) when selecting modified blood components to minimize transfusion‑related adverse events.
Test your knowledge at the end of this chapter with practice questions.
Transfusion of blood components with special modifications or attributes may be warranted in specific clinical settings to reduce the risk of adverse transfusion events. This chapter describes the preparation of irradiated and washed blood components, and the clinical setting in which they are of greatest benefit. The rationale for the universal use of CMV safe blood components is also discussed.
Irradiated blood components
Background and mechanism
Irradiation is a modification applied to cellular blood components to reduce the risk of transfusion-associated graft-versus-host disease (TA-GvHD), a rare but frequently fatal adverse transfusion reaction. This type of modification damages the DNA of T-lymphocytes, preventing them from replicating and reducing the risk of TA-GvHD.1
As irradiation affects component quality, it requires additional regulatory compliance and conscientious management of hospital inventories to provide irradiated cellular blood components to patients with specific clinical indications.2
Clinical significance
TA-GvHD is caused by the transfusion of cellular blood components (e.g., red blood cells, platelets or granulocytes) that contain viable donor T-lymphocytes. When an individual receives cellular blood components from a donor with a similar human leukocyte antigen (HLA) profile, their immune system may not identify the donor T-lymphocytes as foreign (non-self) cells. In this rare situation, donor lymphocytes can then proliferate and attack recipient tissues leading to graft-versus-host disease.
Two populations who have an especially high risk of TA-GvHD include:
-
Recipients of blood components who have known HLA similarities to the donor, such as in the case of red blood cell or platelet donation from family members, or selection of HLA-matched platelet transfusions.
-
Immune compromised recipients, especially those with impaired T-cellular immunity.
Risk for TA-GvHD likely depends more on the degree of HLA similarity between the blood donor and the transfusion recipient than on degree of immune compromise. This is highlighted in a systematic review which challenged the prevalent notion that immune status of the recipient is the main determinant of susceptibility to TA-GvHD.3 Longer component storage time (21 days or more)4 may also be associated with a lower risk of TA-GvHD.
TA-GvHD symptoms may include:
-
fever
-
rash
-
transaminitis
-
pancytopenia
These symptoms usually appear 8–14 days (median 11 days) post-transfusion and progress to irreversible pancytopenia within six weeks of the transfusion.5 Death often occurs 19 to 32 days (median 24 days) after the implicated transfusion.3 Diagnosis is based on clinical presentation, characteristic pathologic changes on skin or liver biopsy and demonstrating the presence of donor lymphocytes in recipient tissues using molecular, cytogenetic, or tissue typing techniques. As TA-GvHD is most often incurable and has a high fatality risk, prevention of this complication is key.
Component processing
While TA-GvHD has rarely been reported following the transfusion of leukoreduced blood components, leukoreduction (a pre-storage filtration process) alone is an insufficient prevention strategy, as the minimum lymphocyte dose capable of causing TA-GvHD is unknown. Most cases of TA-GvHD have been reported following cellular, non-leukoreduced, non-irradiated components that were stored for 10 days or less. As such, the Canadian Standards Association Z902:25, Blood and Blood Components requires that cellular components (i.e., red blood cells, platelets, platelets-pheresis, and granulocytes) for at-risk recipients shall be irradiated or pathogen-reduced using a Health Canada approved procedure to prevent TA-GvHD.6
Irradiation methods
Cellular blood components may be irradiated using a gamma-ray source (e.g., Cesium-137 (Gammacell 1000 or Cobalt-60), or X-ray source (e.g., Raycell). Both techniques must deliver a prescribed dose of radiation to all portions of the blood component unit to ensure complete inactivation of donor lymphocytes, as even a small number of lymphocytes found in peripheral tubing may cause TA-GvHD. The recommended radiation dose is 25 Gy to the central point of the blood pack with a minimum dose of 15 Gy to other parts, with no part receiving more than 50 Gy.6,7 The time required for component irradiation is dependent on the radiation intensity of the source. Commercially available indicator labels are applied to the blood component to verify that an adequate radiation dose has been delivered.
Psoralen treatment also reduces T‑cell proliferation, thereby markedly lowering the risk of TA‑GvHD. Therefore, psoralen‑treated blood components do not require irradiation.1 For more information on psoralen-treated components, see Chapter 19 of the Clinical Guide to Transfusion.
Effects on red blood cells
Irradiation irreparably damages the red blood cell membrane, increasing the rate of potassium loss and precipitating hemolysis with decreased red blood cell recovery. Thus, the red blood cell component storage timeline is shortened post-irradiation. Specifically, these components should be irradiated within 28 days of collection and transfused as soon as possible (no later than 14 days after irradiation and no later than 28 days after collection).6 Certain patient populations may be more susceptible to the effects of hyperkalemia associated with the damage to the red blood cells and may require specially selected irradiated cellular blood components. For more information see the Neonatal and pediatric subsection of this chapter.
Effects on platelets
While some differences in quality parameters have been identified between irradiated and non-irradiated platelet components, these findings have not been significant enough to impact storage guidelines. The expiry of platelet units is not impacted by irradiation.8
Components not requiring irradiation
Plasma which has been frozen (including fresh frozen plasma (FFP)/frozen plasma (FP), cryoprecipitate, and cryosupernatant plasma) and fractionated plasma products have not been associated with TA-GvHD as they do not contain viable white blood cells; thus, they do not require irradiation. Please note that cryosupernatant plasma is no longer available from Canadian Blood Services. More information can be found in the customer letter (#2025-02).
Clinical indications
Cellular blood components requiring irradiation
Use of irradiated cellular blood components is recommended for patients with an increased risk of TA-GvHD, and it is required that the transfusion service shall have a policy indicating which recipients shall receive irradiated cellular blood components and storage periods for these components.2,6 See Table 1 for a summary of the cellular blood components requiring irradiation.
Table 1: Cellular blood components requiring irradiation
| Blood components to be irradiated prior to transfusion to patients at risk for transfusion-associated graft versus host disease (TA-GvHD) |
|---|
|
| Blood components to be irradiated prior to the transfusion to any patient* |
|
|
*Canadian Blood Services does not manufacture untreated platelets from whole blood, however untreated apheresis platelets in PAS-E may be available. See the customer letters: CL #2022-01 and CL #2022-34 for more information. Information on current blood components from Canadian Blood Services may be found in the Circular of Information. †Canadian Blood Services does not provide granulocyte concentrates, but they are available from Héma-Québec (see Chapter 20, of the Clinical Guide to Transfusion). |
Patient populations at risk of TA-GvHD
In 2023, the Irradiation Working Group subcommittee of the Canadian National Advisory Committee (NAC) on Blood and Blood Products developed recommendations for irradiated blood component use in Canada. These recommendations provide the clinical indications for transfusion of irradiated blood components and identify known immunosuppressive medications likely to increase TA-GvHD risk (see Table 2 for a summary).2
Table 2: Quick reference of clinical indications for irradiated blood component transfusion (reproduced from the National Advisory Committee on Blood and Blood Products, Recommendations for use of Irradiated Blood Components in Canada: A NAC and CCNMT Collaborative Initiative, Appendix A)2
| Patient Category | Condition | Duration of irradiated blood requirement |
|---|---|---|
| General population | Directed donation (blood from first- and second- degree relatives)* | NA - product related |
| HLA-selected (matched) platelets | NA- product related | |
| Granulocyte transfusion | NA - product related | |
| Pregnancy, to a fetal recipient | Intrauterine transfusion (IUT) | During the entire pregnancy |
| Pediatrics |
Neonatal exchange transfusion |
Each procedure only |
|
Neonatal small volume (top-up) transfusion:
|
6 months following the EDD | |
|
Congenital severe T-cell immune deficiency
|
Until immunodeficiency ruled out, or life-long if proven immunodeficiency |
|
|
Congenital cardiac abnormalities
|
Until immunodeficiency ruled out, or life-long if proven immunodeficiency | |
| Hematology
|
Hodgkin lymphoma
|
Minimum of 6 months following achievement of remission |
|
Aplastic anemia
|
Unable to recommend a duration following therapy
Minimum of 6 months after cessation of therapy |
|
|
Allogeneic HSCT
|
Until meets criteria for discontinuation
Appropriateness of lifting the indication for irradiation should be reviewed at least yearly by the Transplant Hematologist |
|
|
Autologous bone marrow transplant
|
Until 3 months post-transplant Until 6 months post-transplant |
|
|
CAR-T therapy
|
Until 6 months post-CAR-T cell infusion | |
| Harvest (collection) of stem cells for autologous or allogeneic HSCT (apheresis or bone marrow source), DLI or CAR-T cell therapy |
For 7 days prior to and during the bone marrow or peripheral blood stem cell/lymphocyte collection |
|
|
Medications (generic names listed only) Refer to Section 16 of the Recommendations for use of irradiated blood components in Canada for details. |
Certain chemotherapy/ immunosuppressive agents (generic names listed only)
The product monograph of new immunosuppressive therapeutic agents should be consulted to guide the use of irradiated blood components. |
Minimum of 6 months after cessation of therapy
Unable to recommend a duration following therapy
During therapy and for a minimum of 6 months after cessation of therapy
During therapy and for a minimum 6 months after cessation of therapy
|
*Canadian Blood Services no longer has a directed donations program. See here.
This table was reproduced with permission from the National Advisory Committee on Blood and Blood Products. For more information, please refer to:
Prokopchuk-Gauk, O., Robitaille, N., Tinmouth, A., Shih, A., Musuka, C., Devine, D., & National Advisory Committee on Blood and Blood Products (NAC) and Canadian Clinical Network for Transfusion Medicine (CCNMT). (2023, October 16). Recommendations for use of irradiated blood components in Canada: A NAC and CCNMT collaborative initiative. National Advisory Committee on Blood and Blood Products. https://nacblood.ca/en/resource/recommendations-use-irradiated-blood-components-canada
Special populations and practical considerations
Neonatal and pediatric populations
Neonatal patients may be particularly susceptible to the effects of hyperkalemia associated with the damage to red blood cells in irradiated cellular blood components. Therefore, the freshest possible red blood cells should be chosen for irradiation and, if feasible, irradiation should occur immediately prior to issue. If the red blood cell component is not used immediately, the transfusion service shall have a policy concerning allowable storage time and identify patients for whom previously irradiated units may or may not be used.6
For patients at high risk of complications from hyperkalemia (e.g., pediatric cardiac surgery, neonatal top-up transfusion) or those receiving high-volume transfusions (e.g., intrauterine or neonatal exchange), a single-wash procedure of red blood cells including supernatant removal may be performed before or after irradiation (depending on your institutional protocols) to reduce potassium levels if more than 24 hours has elapsed since the unit was irradiated (learn more about washing procedures below).9-11
For more information on neonatal and pediatric populations, please read Chapter 13 of this Guide.
Other special populations
Irradiation of cellular blood components is not considered necessary for patients with human immunodeficiency virus (HIV) infection, recipients of solid organ transplants, or patients with isolated humoral (B-cell) immune deficiency disorders such as hypogammaglobulinemia.2
Cryopreserved red blood cells
The British guidelines on irradiated blood components state that it is not necessary to irradiate cryopreserved red blood cells as leukocytes do not survive this cryopreservation process. At the time of chapter publication, no cases of TA-GvHD have been reported after transfusion of this component.12
Washing blood components to reduce residual substances
Background and mechanism
Cellular blood components may be modified by washing to reduce the level of residual plasma proteins (e.g., antibodies, serum proteins such as IgA), metabolic byproducts (e.g., potassium, cytokines) or additive solutions. Facilities that modify or transform cellular components, including washing of red blood cells or platelets, require Health Canada registrations.13 Although cellular blood component washing is typically used to prevent or reduce the risk of adverse transfusion events in certain recipients, the washing process shortens the blood component expiration time, lowers cellular yield, and is labour intensive.
Clinical significance
Historically, patients with documented IgA deficiency were transfused with red blood cells manually washed with a minimum of two litres of normal saline due to the concern of an increased risk of anaphylactic reaction with standard red blood cell components. The incidence of anaphylactic reaction with red blood cell transfusion in patients with true IgA deficiency is approximately equivalent to that of the general population (about 1:50,000 transfusion events),14 which suggests that being IgA deficient alone does not increase the risk of an anaphylactic transfusion reaction. Individuals with a history of an anaphylactic transfusion reaction should be tested for IgA deficiency and the presence of anti-IgA.15 In the absence of a history of an anaphylactic (or 2 severe) transfusion reactions, most practitioners do not recommend testing patients who are low in IgA for the presence of anti-IgA. There is little evidence to suggest that washed red cells should be transfused to IgA-deficient patients in the absence of previous reactions.16 For more information, see the publication, Anaphylactic transfusion reactions and IgA deficiency.
Component processing
Washed red blood cell components
Red blood cell washing is a modification applied to a red blood cell component that has undergone pre-storage leukoreduction by filtration at Canadian Blood Services. The red blood cells are washed several times with a compatible solution and then resuspended prior to transfusion. The volume of fluid required is dependent on the indication for the washed component but typically involves up to three litres of wash solution. Washing may be performed using a validated manual (open-system) or automated (closed-system) procedure using specialized blood processing equipment. Washing red blood cell components markedly reduces the levels of plasma proteins, antibodies, and electrolytes in the component.17
It takes approximately two hours to process each red blood cell unit washed by either manual or automated methods. These processes require internal validation to demonstrate significant protein reduction and appropriate red blood cell recovery. Due to red blood cell loss during washing, recoveries as low as 85% can be expected.18
According to the Canadian Standards Association Z902:25, Blood and Blood Components6, standard 7.5.3.2:
“Red blood cells - washed shall be prepared by a method known to retain at least 75% of the red cells that were in the original red blood cells and yield a hematocrit of not more than 0.8 L/L.”
Washed red blood cells at Canadian Blood Services
Canadian Blood Services is able to provide washed red blood cells upon request using its closed-system (sterile) automated wash procedure that extends the permissible component storage duration to 7 days post-wash.17,19 In this procedure, red blood cell units within the first two weeks of storage are washed, then resuspended in 100 ml of AS-3 solution, using the ACP-215 (See Figure 1). Depending on the indication and wash procedure, the final components are labelled “Washed Red Blood Cells Leukocytes Reduced” or “Extra Washed Red Blood Cells Leukocytes Reduced (IgA DEF (deficient)).” An initial wash uses approximately two litres of saline; a second wash with this same volume is performed to produce IgA-deficient washed red blood cells. Red blood cell washing is not available at all Canadian Blood Services manufacturing sites; thus, coordination with distribution sites to obtain washed or extra-washed cells may be required.
The current automated methodology used by Canadian Blood Services for “extra wash” red blood cells has been validated to provide a component that meets the definition of being IgA deficient, containing less than 0.05 mg/dL of IgA protein, meeting the Canadian Standards Association Z902:25, Blood and Blood Components.6,18,2
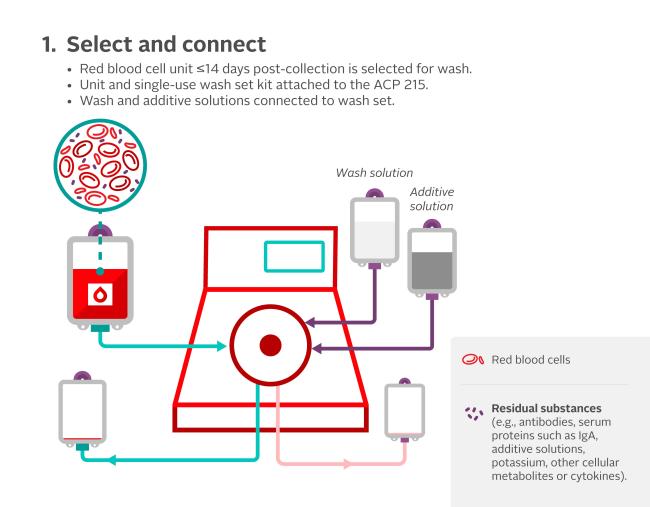
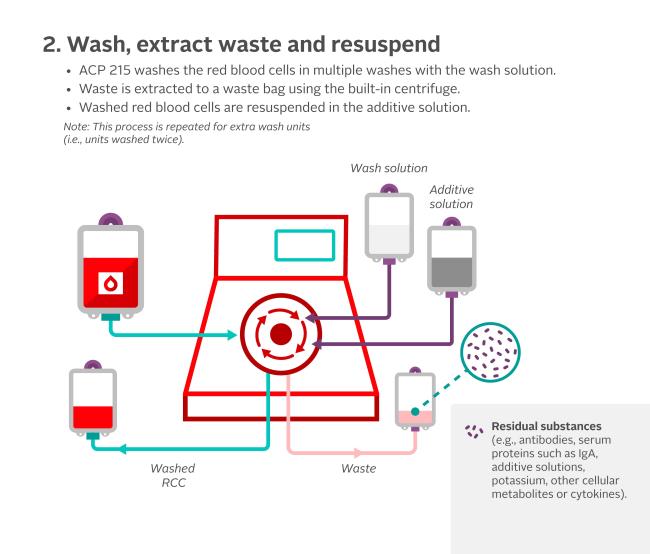
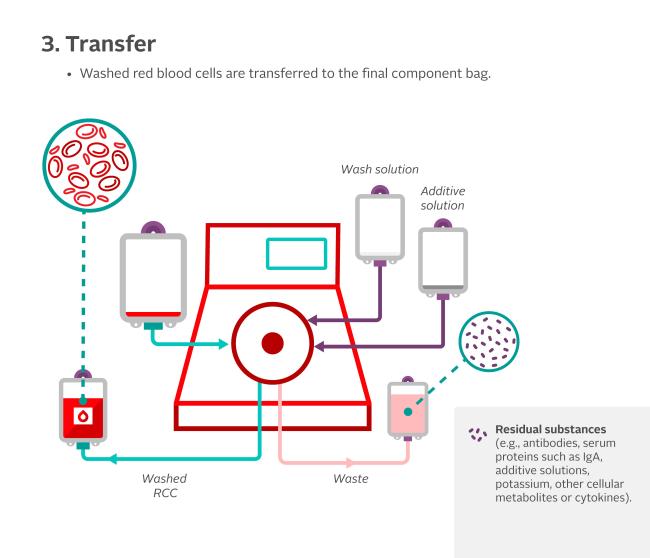

Figure 1: Closed-system, automated washing procedure for red blood cells at Canadian Blood Services.
Washed red blood cells at hospital sites
Hospital sites may also wash leukoreduced red blood cells. Washing may be performed manually (open-system) or with an automated system (closed-system), if available. Typically, only open-systems are available within hospital sites, which shortens the expiry of the red blood cell unit to 24 hours from the start of the washing process. This short expiry is required if an open system (non‑sterile) process is used for washing as the risk of bacterial contamination is increased. A typical manual wash procedure begins by spiking the unit to attach a transfer bag followed by centrifugation. The supernatant is then removed and 200–250 mL of wash solution is added. The unit is centrifuged again and the wash solution is extracted. This wash-and-extraction step is repeated two additional times, after which the red blood cells are resuspended in the final solution. If an automated washing system is available, this procedure should follow the equipment manufacturer specifications and instructions.
Red blood cell additive depletion
Most hospital-based transfusion medicine services that provide washed red blood cells will also provide a “single-washed” or “additive depleted” red blood cell component (these terms are interchangeable). In this process, normal saline is added to the red blood cell bag before it is centrifuged to remove the plasma supernatant and then resuspended in a small volume of compatible fluid [5% albumin, 0.9% sodium chloride], or ABO type compatible plasma [frozen plasma, psoralen-treated plasma, or solvent detergent plasma], as appropriate prior to transfusion to a desired hematocrit.
Like manually washed red blood cells, these blood components expire within 24 hours and may be requested:
-
Prior to neonatal exchange transfusion or massive transfusion in neonatal/pediatric patients to minimize the amount of additive solution and/or potassium in the component.10
-
To mitigate recurrent moderate or severe medication-refractory febrile, allergic, or hypotensive reactions by removing potentially responsible plasma proteins or cytokines.
Washed platelet components
Platelet components may also undergo a single-wash to remove plasma and supernatant substances such as antibodies or other serum proteins that may be harmful to some transfusion recipients. Platelets prepared from whole blood donations or by apheresis may be washed using normal saline, or saline buffered with anticoagulant citrate dextrose, solution A (ACD-A) or citrate. The washing may be a manual or automated process, depending on equipment availability.
As there is an increased risk of bacterial contamination and possible metabolic damage to platelets, washed platelets must be transfused within four hours of beginning the wash procedure. Since the washing procedure itself takes at least two hours, the timing of the washing procedure with respect to the timing of the transfusion event must be carefully coordinated. While the viability and efficacy of platelet transfusion is not significantly affected with washing, there is considerable platelet loss (up to 20%) due to platelet activation.21 Canadian Blood Services does not currently provide washed platelet components. Therefore, hospitals requiring these components must prepare them in the hospital blood bank.
There is high platelet loss associated with washing, so some institutions may use plasma volume reduction with resuspension in a compatible fluid as an alternative. This process may reduce mild-moderate allergic reactions but will not entirely prevent anti-IgA associated anaphylaxis due to incomplete IgA removal.22
Plasma reduction of platelets may also be used prior to transfusion of ABO-incompatible platelets in a shortage situation to reduce the risk of isohemagglutinin-mediated red blood cell hemolysis in platelet recipients, or to volume-reduce platelets for neonatal recipients with very small blood volumes.
For those who develop an allergic transfusion reaction thought to be secondary to psoralens in pathogen-reduced platelets, non-pathogen reduced PAS-E suspended apheresis platelets are an alternative option.
Clinical indications
Washed red blood cells
Current indications for washed red blood cells include:23
-
Washed: Recipient with a history of severe or repeated reactions to blood components (unresponsive to pre-medication).
-
Extra Wash (IgA deficient): IgA-deficient recipient with anti-IgA who have previously had a major allergic reaction following transfusion of labile blood products24
The administration processes for washed red blood cells are the same as those for unwashed red blood cells, with the exception of a reduced expiry time. Similarly, the risks associated with standard red blood cell transfusion also apply to washed red blood cells, although the incidence of febrile and allergic reactions is reduced due to the removal of white blood cells and plasma from the component. The risk of bacterial contamination is slightly higher if an open washing system is used.
Washed platelets
Washed platelets may be indicated for:
-
IgA-deficient patients with a severe allergic reaction and anti-IgA, when platelets from an IgA-deficient donor are unavailable.
-
Patients with a history of anaphylactic transfusion reactions of unknown etiology.
-
Recurrent and/or severe febrile or allergic transfusion reactions, if not ameliorated by pre-transfusion medications or responsive to plasma reduced platelets.
In patients with anaphylaxis with transfusion or two severe allergic reactions, and proven anti-IgA antibodies, the preferred platelet component would be one collected from an IgA deficient donor.
Cytomegalovirus (CMV)-safe components
Background and mechanism
CMV, also known as human herpesvirus-5, is a large, enveloped, double-stranded DNA virus. Primary CMV infection can occur following contact with bodily fluids (e.g., saliva, breastmilk or urine) of an individual actively shedding viral DNA, following transfusion of unmodified cellular blood components (transfusion-transmitted CMV infection; TT-CMV) or from transplantation of organs and tissues from donors known to have previously been infected with CMV.24 Prior to the implementation of CMV reduction strategies, potential transmission of TT-CMV was a concern in immune compromised blood recipients.
Clinical significance
In a healthy individual, primary CMV infection is often asymptomatic or results in a mild, non-specific illness similar to mononucleosis, while in immune compromised individuals, it can manifest as CMV disease, which can include life-threatening pneumonia, hepatitis and colitis. Rarely, primary CMV infection in an expectant mother may lead to congenital CMV in the newborn infant.
Individuals who recover from a primary CMV infection develop an immune response and produce detectable CMV IgG antibodies after approximately six to eight weeks (the window period) after contracting the virus. During the window-period, the amount of viral DNA present in the plasma may be so low that it is below detectable levels through lab testing. Following recovery from infection, the virus then becomes dormant (latent) in the monocyte population of white blood cells and may reactivate at a later time. Within the blood donor population, it is these residual white blood cells that carry the risk of TT-CMV transmission.
The prevalence of CMV-seropositive individuals is estimated to be 53% in the Canadian population25, and ranges from 20% to 100% in adults worldwide.26 The seroconversion rate among Canadian Blood Services’ donors is approximately 0.7% annually.27
Component processing
To reduce the potential transmission of TT-CMV in Canada, CMV IgG serologic screening of blood donors was implemented in the mid-1980s, prior to standard pre-storage leukoreduction of cellular blood components. However, CMV serologic testing does not guarantee that a CMV seronegative component will truly be “CMV negative” and the concentration of CMV DNA required to cause TT-CMV infection is unknown.28 CMV DNA has been detected in 0.04% of units labelled as “CMV-seronegative,” with recent evidence suggesting that the greatest concentration of CMV DNA is present in the plasma within the first year of seroconversion following primary infection.29
In 1997, use of leukoreduction filters became standard at Canadian Blood Services; thus, CMV IgG seronegative blood components were also leukoreduced. Canadian Blood Services used a dual-CMV reduction strategy of identifying CMV seronegative donors plus leukoreduction, which continued through to 2017, until strong evidence was presented that a singular strategy was effective.30,31 More details about these blood components can be found on Canadian Blood Services’ Circular of Information.
It is now accepted that blood components that are CMV-seronegative or leukoreduced or psoralen-treated are considered CMV-safe.32 At the time of this publication, Canadian Blood Services does not perform nucleic acid tests for CMV DNA.
Red blood cells
Red blood cells produced by the buffy coat method are rendered CMV-safe by the leukofiltration step during component processing. To learn more about this method of processing, see Chapter 2 of this Guide.
Platelets
Platelets produced by the buffy coat method are rendered CMV-safe by the leukofiltration step during component processing, and platelets produced by apheresis are leukoreduced during the apheresis procedure. To learn more about this method of process, see Chapter 2 of this Guide.
Pooled platelets and apheresis platelets which are psoralen treated are also considered CMV-safe. Psoralen treatment results in damage to CMV DNA; therefore, the transmission concern during the window period or reactivation with products that have undergone leukoreduction and serological testing is not present for components.28,29 More details can be found on Canadian Blood Services’ Circular of Information and in Chapter 19 of this Guide.
Plasma
Plasma is considered CMV-safe without additional filtration as it is acellular due to the whole blood processing and plasma freezing methods.
Clinical indications
Clinical evidence supporting best practices to mitigate transfusion-transmitted CMV (TT-CMV) risk
Before leukoreduction and CMV IgG serologic screening were adopted, the incidence of TT-CMV was reported to be 10–60%, and was typically seen three to eight weeks after transfusion of an infected cellular component.33 Based on test sensitivity and leukoreduction efficiency, each method was found to have an estimated residual risk of CMV transmission of approximately 1.5–3% per transfused recipient.34 However, in an Australian study, the residual risk of TT-CMV from leukoreduced red blood cells and platelets (combined) was shown to be much lower: 1 in 13.5 million units transfused.30 In Canada, the residual risk of TT-CMV is also very low at 1 in 680,000 red blood cell units transfused and eliminated from any psoralen-treated, pathogen reduced components such as platelets.31
Observational studies in allogeneic hematopoietic stem cell transplant patients have not demonstrated any increased risk of TT-CMV with leukoreduced and CMV-untested (CMV-safe) cellular components.35-38 In practice, the risk of CMV reactivation and primary infection from the environment in the immediate post-hematopoietic stem cell transplant period has led to routine monitoring of recipients for CMV viremia, with initiation of pre-emptive treatment if increasing CMV copies are detected. A small prospective study evaluated TT-CMV risk in very low-birth-weight infants comparing leukoreduction-only versus CMV-seronegative plus leukoreduction—both groups had zero observed transmissions, though the leukoreduced-only cohort was small (n = 20). To date, no published comparative studies have been conducted in the context of intrauterine transfusions (IUT).39
In July 2025, the National Advisory Committee on Blood and Blood Products (NAC) CMV Subcommittee published the following statement:
“The NAC recommends that CMV safe (leukoreduced) and CMV IgG seronegative products be considered equivalent for blood components that are produced by Canadian Blood Services.” 32
Following this statement the NAC removed their recommendation for maintaining a separate inventory of CMV‑seronegative products for IUT or exploring feasibility of CMV NAT testing.32 This shift in practice now aligns with that of international countries where, despite a higher CMV population seroprevalence, leukoreduced blood components are considered CMV safe for all indications – including IUT.39 Further, general consensus by treaters in Canada has supported prioritization of phenotype matched units in the context of maternal alloimmunization over CMV seronegative testing status for patients undergoing IUT.32
Leukoreduced (CMV safe) blood components are also recommended for transfusion of very-low birthweight infants, as transmission of CMV in breastmilk appears to be the greatest risk factor for CMV disease in neonates.40
Importantly, this NAC recommendation is not applicable to granulocytes which are produced by Héma-Québec. For guidance pertaining to granulocytes, readers are referred to Héma-Québec and Comité consultatif national de médecine transfusionnelle documents.
Practice Questions
Below are knowledge check questions hosted on Microsoft forms. These questions are designed to help reinforce key concepts and support your learning. Your responses will be anonymous, and scores for this learning assessment will be presented to you for self-assessment purposes. These scores and your answers will be recorded in Microsoft Forms and will be used to assess the impact of knowledge check questions as an additional educational resource in the Clinical Guide to Transfusion for quality improvement of this resource.
If you have any questions about these practice questions or suggestions for improvement, please contact us through the Feedback form.
If you are an educator and would like to use these questions in your teaching, please acknowledge Canadian Blood Services.
Additional resources
Presentation by Dr. Jeannie Callum
Transfusion-transmitted cytomegalovirus: Can you confidently abandon CMV seronegative products in the modern era of pre-storage leukoreduction?
This presentation by Dr. Jeannie Callum examines the biology and epidemiology of CMV, history of transfusion-transmitted CMV, and evidence that supports leukoreduction as a sole strategy for CMV prevention in blood and blood components. For the most recent NAC recommendations on CMV blood components, see their website.
-
Full slide deck presentation with audio (recorded July 2017, 25:05 minutes)
-
Condensed presentation with audio (recorded July 2017, 11:04 minutes)
-
Download the slide deck for Dr. Callum’s presentation and use for your own presentations.
Continuing professional development credits
Fellows and health-care professionals who participate in the Canadian Royal College's Maintenance of Certification (MOC) program can claim the reading of the Clinical Guide to Transfusion as a continuing professional development (CPD) activity under Section 2: Individual learning. Learners can claim 0.5 credits per hour of reading to a maximum of 30 credits per year.
Medical laboratory technologists who participate in the Canadian Society for Medical Laboratory Science’s Professional Enhancement Program (PEP) can claim the reading of the Clinical Guide to Transfusion as a non-verified activity.
Suggested Citation
Syed T, Prokopchuk-Gauk O & Solh Z. Irradiated, washed and CMV-tested blood components. In: Khandelwal A, Brooks K, editors. Clinical Guide to Transfusion [Internet]. Ottawa: Canadian Blood Services, 2026 [cited YYYY MO DY]. Chapter 15. Available from: Irradiated, washed and CMV-tested blood components | Professional Education
If you have questions about the Clinical Guide to Transfusion or suggestions for improvement, please contact us through the Feedback form.
References
- Cid, J. (2017). Prevention of transfusion-associated graft-versus-host disease with pathogen-reduced platelets with amotosalen and ultraviolet A light: a review. Vox Sang, 112(7), 607-613. https://doi.org/10.1111/vox.12558
- Prokopchuk-Gauk O, R. N., Tinmouth A, Shih A, Musuka C, Devine D, et al. (2023). Recommendations for use of Irradiated Blood Components in Canada: A NAC and CCNMT Collaborative Initiative. https://nacblood.ca/en/resource/recommendations-use-irradiated-blood-components-canada
- Kopolovic, I., Ostro, J., Tsubota, H., Lin, Y., Cserti-Gazdewich, C. M., Messner, H. A., Keir, A. K., DenHollander, N., Dzik, W. S., & Callum, J. (2015). A systematic review of transfusion-associated graft-versus-host disease. Blood, 126(3), 406-414. https://doi.org/10.1182/blood-2015-01-620872
- Mykhailova, O., Turner, T. R., Olafson, C., Howell, A., Nahirniak, S. N., Wizniak, J., Gerges, H. Y. N., Baldwin, T., Clarke, G., & Acker, J. P. (2021). Hypothermic storage of leukoreduced red blood cells for greater than 21 days is a safe alternative to irradiation [https://doi.org/10.1111/trf.16273]. Transfusion, 1-11. https://doi.org/https://doi.org/10.1111/trf.16273
- Centers for Disease Control and Prevention. (2026). Biovigilance component hemovigilance module protocol version 3.0. Retrieved February 2026, from https://www.cdc.gov/nhsn/pdfs/biovigilance/bv-hv-protocol-current.pdf
- Canadian Standards Association Group. (2025). CAN/CSA-Z902:25 Blood and blood components. CSA. https://www.csagroup.org/store/product/CAN-CSA-Z902%3A25/
- Pelszynski, M. M., Moroff, G., Luban, N. L., Taylor, B. J., & Quinones, R. R. (1994). Effect of gamma irradiation of red blood cell units on T-cell inactivation as assessed by limiting dilution analysis: implications for preventing transfusion-associated graft-versus-host disease. Blood, 83(6), 1683-1689. http://www.ncbi.nlm.nih.gov/pubmed/8123860
- Tynngard, N., Studer, M., Lindahl, T. L., Trinks, M., & Berlin, G. (2008). The effect of gamma irradiation on the quality of apheresis platelets during storage for 7 days. Transfusion, 48(8), 1669-1675. https://doi.org/10.1111/j.1537-2995.2008.01746.x
- Swindell, C. G., Barker, T. A., McGuirk, S. P., Jones, T. J., Barron, D. J., Brawn, W. J., Horsburgh, A., & Willetts, R. G. (2007). Washing of irradiated red blood cells prevents hyperkalaemia during cardiopulmonary bypass in neonates and infants undergoing surgery for complex congenital heart disease. Eur J Cardiothorac Surg, 31(4), 659-664. https://doi.org/10.1016/j.ejcts.2007.01.014
- Vraets, A., Lin, Y., & Callum, J. L. (2011). Transfusion-associated hyperkalemia. Transfus Med Rev, 25(3), 184-196. https://doi.org/10.1016/j.tmrv.2011.01.006
- Parkman, R., Mosier, D., Umansky, I., Cochran, W., Carpenter, C. B., & Rosen, F. S. (1974). Graft-versus-host disease after intrauterine and exchange transfusions for hemolytic disease of the newborn. N Engl J Med, 290(7), 359-363. https://doi.org/10.1056/NEJM197402142900703
- Foukaneli, T., Kerr, P., Bolton-Maggs, P. H. B., Cardigan, R., Coles, A., Gennery, A., Jane, D., Kumararatne, D., Manson, A., New, H. V., Torpey, N., & Committee, t. B. (2020). Guidelines on the use of irradiated blood components. Br J Haematol, 191(5), 704-724. https://doi.org/https://doi.org/10.1111/bjh.17015
- Health Canada. (2014, February 21, 2023). Guidance document: Blood regulations. Retrieved September 17 from https://www.canada.ca/en/health-canada/services/drugs-health-products/biologics-radiopharmaceuticals-genetic-therapies/applications-submissions/guidance-documents/blood-regulations/guidance-document-blood-regulations.html
- Sandler, S. G. (2015). Immunosuppressive medication and alloimmunization to red blood cell antigens. Transfusion, 55(1), 224. https://doi.org/10.1111/trf.12930
- Khandelwal A, C. G., Goldman M. (2021). Anaphylactic transfusion reactions and IgA deficiency. https://profedu.blood.ca/en/transfusion/publications/anaphylactic-transfusion-reactions-and-iga-deficiency
- Cardigan, R., New, H. V., Tinegate, H., & Thomas, S. (2020). Washed red cells: theory and practice. Vox Sang, 115(8), 606-616. https://doi.org/https://doi.org/10.1111/vox.12971
- Acker, J. ( 2015). Bath time for blood cells: improving the red blood cell washing process, Research Unit. Canadian Blood Services Retrieved March 3 from https://www.blood.ca/en/hospital-services/transfusion-practice/research-units/bath-time-blood-cells-improving-red-blood
- Hansen, A. L., Turner, T. R., Kurach, J. D., & Acker, J. P. (2015). Quality of red blood cells washed using a second wash sequence on an automated cell processor. Transfusion, 55(10), 2415-2421. https://doi.org/10.1111/trf.13166
- Acker, J. P., Hansen, A. L., Yi, Q. L., Sondi, N., Cserti-Gazdewich, C., Pendergrast, J., & Hannach, B. (2016). Introduction of a closed-system cell processor for red blood cell washing: postimplementation monitoring of safety and efficacy. Transfusion, 56(1), 49-57. https://doi.org/10.1111/trf.13341
- Khandelwal, A., Clarke, G., Goldman, M. (2021). Anaphylactic transfusion reactions and IgA deficiency. Retrieved April 22, 2022, from https://professionaleducation.blood.ca/en/transfusion/publications/anaphylactic-transfusion-reactions-and-iga-deficiency
- Vesilind, G. W., Simpson, M. B., Shifman, M. A., Colman, R. E., & Kao, K. J. (1988). Evaluation of a centrifugal blood cell processor for washing platelet concentrates. Transfusion, 28(1), 46-51. http://www.ncbi.nlm.nih.gov/pubmed/3341066
- Schoenfeld, H., Muhm, M., Doepfmer, U. R., Kox, W. J., Spies, C., & Radtke, H. (2005). The functional integrity of platelets in volume-reduced platelet concentrates. Anesth Analg, 100(1), 78-81. https://doi.org/10.1213/01.ANE.0000140239.43116.30
- Canadian Blood Services. (2020). Circular of Information for the Use of Human Blood Components: Red Blood Cells, Leukocytes Reduced (LR). https://www.blood.ca/en/hospital-services/products/component-types/circular-information
- Héma-Québec. Washed red blood cells. Héma-Québec. Retrieved September 17, 2025 from https://www.hemaquebec.ca/en/health-professionals/labile-blood-products/washed-red-blood-cells
- Lieberman, L., Devine, D. V., Reesink, H. W., Panzer, S., Wong, J., Raison, T., Benson, S., Pink, J., Leitner, G. C., Horvath, M., Compernolle, V., Prado Scuracchio, P. S., Wendel, S., Delage, G., Nahirniak, S., Dongfu, X., Krusius, T., Juvonen, E., Sainio, S., . . . Triulzi, D. (2014). Prevention of transfusion-transmitted cytomegalovirus (CMV) infection: Standards of care. Vox Sang, 107(3), 276-311. https://doi.org/10.1111/vox.12103
- Public Health Agency of Canada. (2011). Pathogen Safety Data Sheets: Infectious Substances - Cytomegalovirus Retrieved March 3 from http://www.phac-aspc.gc.ca/lab-bio/res/psds-ftss/cytomegalovirus-eng.php
- O'Brien, S., Fearon, M., Nahirniak, S., Scalia, V., & Preiksaitis, J. (2015). Prevalence and incidence of cytomegalovirus in blood donors and transplant patients. In Poster presented at Canadian Society for Transfusion Medicine Conference (CSTM) "Where Past and Future Meet".
- Ziemann, M., Krueger, S., Maier, A. B., Unmack, A., Goerg, S., & Hennig, H. (2007). High prevalence of cytomegalovirus DNA in plasma samples of blood donors in connection with seroconversion. Transfusion, 47(11), 1972-1983. https://doi.org/10.1111/j.1537-2995.2007.01420.x
- Ziemann, M., Heuft, H. G., Frank, K., Kraas, S., Gorg, S., & Hennig, H. (2013). Window period donations during primary cytomegalovirus infection and risk of transfusion-transmitted infections. Transfusion, 53(5), 1088-1094. https://doi.org/10.1111/trf.12074
- Seed, C. R., Wong, J., Polizzotto, M. N., Faddy, H., Keller, A. J., & Pink, J. (2015). The residual risk of transfusion-transmitted cytomegalovirus infection associated with leucodepleted blood components. Vox Sang, 109(1), 11-17. https://doi.org/10.1111/vox.12250
- O'Brien, S., Yi, Q. L., & Fearon, M. A. (2017). Residual Risk of Cytomegalovirus After Leukoreduction in the Canadian Blood Supply. CSTM Annual Meeting, Ottawa.
- Nahirniak S, C. G., Lieberman L, Wall D, Preiksaitis J,. (2025, May 4, 2017 [updated 2025 07 17]). Transfusion and Cytomegalovirus in the Canadian Blood System Supported by Canadian Blood Services*. National Advisory Committee on Blood and Blood Products. https://nacblood.ca/en/resource/transfusion-and-cytomegalovirus-canadian-blood-system-supported-canadian-blood-services
- Wu, Y., Zou, S., Cable, R., Dorsey, K., Tang, Y., Hapip, C. A., Melmed, R., Trouern-Trend, J., Wang, J. H., Champion, M., Fang, C., & Dodd, R. (2010). Direct assessment of cytomegalovirus transfusion-transmitted risks after universal leukoreduction. Transfusion, 50(4), 776-786. https://doi.org/10.1111/j.1537-2995.2009.02486.x
- Vamvakas, E. C. (2005). Is white blood cell reduction equivalent to antibody screening in preventing transmission of cytomegalovirus by transfusion? A review of the literature and meta-analysis. Transfus Med Rev, 19(3), 181-199. http://www.ncbi.nlm.nih.gov/pubmed/16010649
- Hall, S., Danby, R., Osman, H., Peniket, A., Rocha, V., Craddock, C., Murphy, M., & Chaganti, S. (2015). Transfusion in CMV seronegative T-depleted allogeneic stem cell transplant recipients with CMV-unselected blood components results in zero CMV transmissions in the era of universal leukocyte reduction: a UK dual centre experience. Transfus Med. https://doi.org/10.1111/tme.12219
- Kekre, N., Tokessy, M., Mallick, R., McDiarmid, S., Huebsch, L., Bredeson, C., Allan, D., Tay, J., Tinmouth, A., & Sheppard, D. (2013). Is cytomegalovirus testing of blood products still needed for hematopoietic stem cell transplant recipients in the era of universal leukoreduction? Biol Blood Marrow Transplant, 19(12), 1719-1724. https://doi.org/10.1016/j.bbmt.2013.09.013
- Nash, T., Hoffmann, S., Butch, S., Davenport, R., & Cooling, L. (2012). Safety of leukoreduced, cytomegalovirus (CMV)-untested components in CMV-negative allogeneic human progenitor cell transplant recipients. Transfusion, 52(10), 2270-2272. https://doi.org/10.1111/j.1537-2995.2012.03739.x
- Thiele, T., Kruger, W., Zimmermann, K., Ittermann, T., Wessel, A., Steinmetz, I., Dolken, G., & Greinacher, A. (2011). Transmission of cytomegalovirus (CMV) infection by leukoreduced blood products not tested for CMV antibodies: a single-center prospective study in high-risk patients undergoing allogeneic hematopoietic stem cell transplantation (CME). Transfusion, 51(12), 2620-2626. https://doi.org/10.1111/j.1537-2995.2011.03203.x
- Clarke, G., Bodnar, M., Lozano, M., Nadarajan, V. S., Lee, C., Baud, D., Canellini, G., Gleich-Nagel, T., Torres, O. W., Rey, P. L., Bub, C. B., Kutner, J. M., Castilho, L., Saifee, N. H., Delaney, M., Nester, T., Wikman, A., Tiblad, E., Pierelli, L., . . . Lieberman, L. (2020). Vox Sanguinis International forum on the selection and preparation of blood components for intrauterine transfusion. Vox Sang, 115(8), e18-e38. https://doi.org/https://doi.org/10.1111/vox.12901
- Josephson, C. D., Caliendo, A. M., Easley, K. A., Knezevic, A., Shenvi, N., Hinkes, M. T., Patel, R. M., Hillyer, C. D., & Roback, J. D. (2014). Blood transfusion and breast milk transmission of cytomegalovirus in very low-birth-weight infants: a prospective cohort study. JAMA Pediatr, 168(11), 1054-1062. https://doi.org/10.1001/jamapediatrics.2014.1360